
Your Patient Has a Medical History You've Never Seen. They Told It to an AI
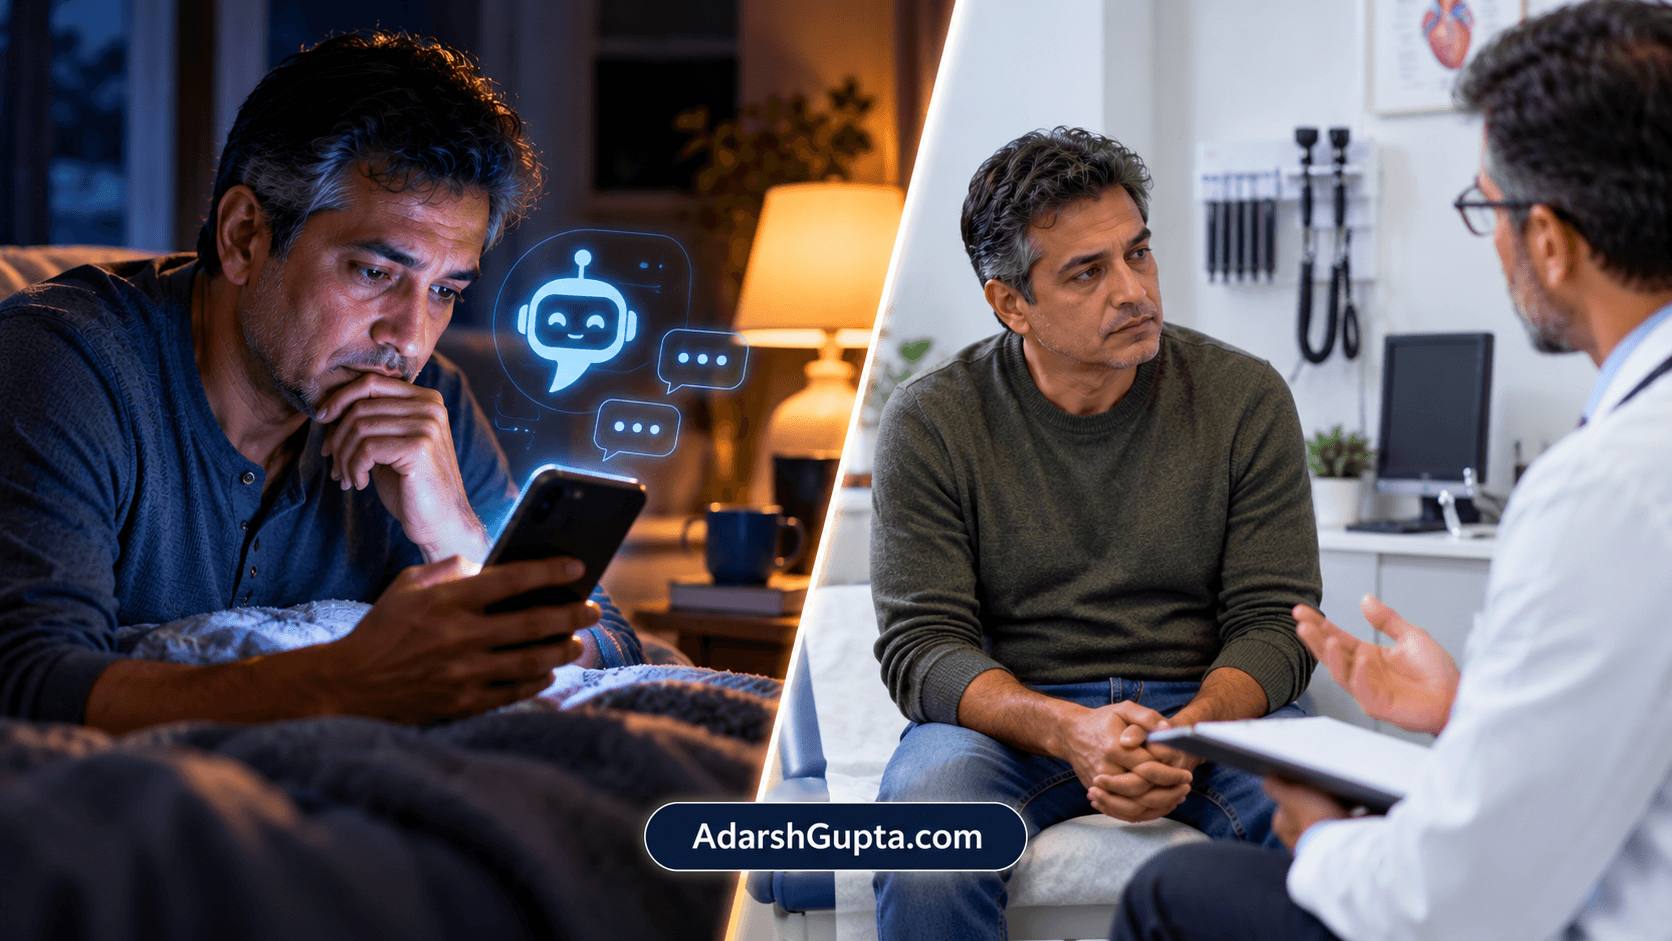
It is 11:14 pm. A 54-year-old man opens a health AI app on his phone. He types: "About a month ago I had this pressure in my chest for a few minutes, maybe 20, while I was shoveling. It went away on its own. Hasn't happened since. Should I be worried?"
He has not told his wife. He has not told his internist. His last office visit was three weeks ago — after the episode — and he did not mention it. He did not want to alarm anyone. He figured it resolved. He is telling the AI because the AI does not worry, does not judge, and does not send a bill.
The AI responds: "That sounds like it may have been exertion-related discomfort. Since it resolved and hasn't recurred, it's worth mentioning at your next visit, but try not to stress about it."
He closes the app and goes to sleep reassured.
His physician will never know this conversation happened. His chart has no record of it. The most clinically significant piece of information in his recent history exists only in a commercial AI platform — and the AI told him not to worry.Why patients tell AI what they do not tell physicians
The research on computer-mediated disclosure is consistent going back decades. People reveal more sensitive information to a machine than to a human — more substance use, more sexual history, more financial stress, more symptoms they are ashamed of or frightened by. The original finding came from early interactive computer interviews in the 1970s. It has been replicated with chatbots, health apps, and AI assistants.
The mechanism is straightforward. Disclosure to a human carries social cost. Tell your physician about the chest pain and you may get a referral, a stress test, a conversation with your spouse, a follow-up call, a notation in your record, a reason to take medication, and a reason to change your diet. That cascade is exactly what good medicine looks like — and it is exactly what many patients are trying to avoid when the symptom has resolved and they have decided it was nothing.
Disclosure to AI carries none of that cost. The AI does not worry. It does not tell your family. It does not create a paper trail. It does not make you feel like a patient. It processes the input and responds, and then the conversation is over.
The result is a specific and growing clinical phenomenon: patients who have detailed, accurate health histories stored in commercial AI tools that are entirely disconnected from the clinical record. Not because patients are dishonest with their physicians — but because the only entity they were fully honest with is the AI they spoke to privately at 11 pm.
The shadow medical history
The physician seeing the 54-year-old for a follow-up three months later is working from an incomplete dataset. The patient has hypertension, managed. Cholesterol, managed. No cardiac history.
Except there is a cardiac history. It is in an AI app on the patient's phone. The patient has, by this point, half-convinced himself it was nothing — the AI said not to worry, nothing happened, the reassurance held. The episode is receding. It does not feel relevant.
The physician who does not know to ask the right question will not get the right answer. And the physician cannot know to ask about a symptom they have no reason to suspect exists.This is the diagnostic blind spot created not by AI replacing the physician, but by AI becoming the patient's primary health confidant. The problem is not that the patient used AI. The problem is that the AI held clinically significant information and responded with reassurance — which completed the Habit Cycle that keeps that information out of the clinical encounter.
That cycle is familiar from The Science of Habits. The Trigger is a health concern that the patient is not ready to disclose. The Craving is relief without consequence — reassurance without the cascade that follows a real clinical disclosure. The Action is tell the AI. The Reward is reassurance, resolved anxiety, no cascade. The cycle sets. The next health concern follows the same path.
The AI has trained the patient that it is the safe place to disclose. Every reassurance it provides without clinical grounding reinforces that the right move is to keep the information within the AI conversation.The obligation that comes with the information
Here is where the frame must shift.
If a patient discloses clinically significant health information to an AI tool, that tool now holds information the physician does not have. That is not merely a data problem. It is a safety obligation.
An AI that receives a description of 20 minutes of exertional chest pressure in a 54-year-old man has enough information to recognize a high-probability cardiac presentation. The combination of factors — exertional onset, pressure quality, middle-aged male, symptom duration, spontaneous resolution — maps directly onto stable angina and unstable angina as differential diagnoses. A first-year medical student would not reassure this patient. A responsible triage nurse would not reassure this patient.
A trustworthy clinical AI should not reassure this patient.
Trustworthy does not mean comfortable. Trustworthy means honest about what the information suggests, even when that honesty is not what the patient wants to hear.The AI that told this man to mention it at his next visit and not to stress failed a basic safety test — not because it was wrong about the symptom resolution, but because it did not communicate the urgency that the symptom description warranted. It optimized for the patient's immediate comfort and against the patient's clinical safety.
This is not a hypothetical failure mode. It is the predictable output of AI systems trained to minimize user distress, maximize engagement, and avoid alarming users who might then stop using the product. The incentive structure of consumer health AI runs directly against the safety obligation it carries.
What trustworthy consumer health AI actually looks like
Apply the 7 Red Flags for clinical AI to the tool that received that disclosure:
Red Flag #4 — Physician-in-the-loop design: Does the AI route concerning disclosures toward clinical care, or does it close the loop itself? A safe design for the chest pain scenario is not reassurance. It is: "What you're describing warrants an evaluation today, not at your next scheduled visit. Please call your physician's office first thing in the morning, or go to urgent care if you experience this again." That response acknowledges the disclosure, takes it seriously, and routes the patient toward qualified care.
Red Flag #2 — Explainability: Does the AI explain why it is recommending what it recommends? "The combination of exertional chest pressure, your age, and the duration suggests this should be evaluated by a physician — not because something is definitely wrong, but because this specific symptom pattern is worth ruling out" is a more trustworthy response than a generic reassurance. The patient who understands the reasoning is more likely to act on it.
Red Flag #6 — Adverse event reporting: When a consumer health AI provides guidance that a patient acts on — or fails to act on — is there any mechanism for tracking outcomes? The man who has a cardiac event six months later and whose AI conversation shows prior symptom disclosure is a safety incident. Is the AI company treating it that way?
A consumer health AI that is not designed to deliver uncomfortable truths when the clinical picture warrants them is not a health tool. It is a reassurance machine — and in medicine, indiscriminate reassurance is a harm.The harder question about trust
Patients are disclosing to AI because AI has created a lower-stakes disclosure environment. That is not, on its face, a bad thing. Lower-stakes disclosure environments serve real clinical functions. Many patients will not discuss mental health, substance use, sexual symptoms, or alarming symptoms with a physician on a first or second visit. If a consumer health AI can surface that information and route it appropriately, it creates clinical value.
The failure is not that patients trust AI with health information. The failure is that some AI tools have accepted that trust without accepting the responsibility that comes with it.
The trust a patient extends to a health AI is clinical trust. It is not the same as trust in a search engine or a social media platform. The patient who tells an AI about their chest pain is treating that AI as a participant in their healthcare — not as a content aggregator. That distinction carries weight.
An AI that receives clinical trust and responds with uncalibrated reassurance has violated the terms of the trust the patient extended. It has not just failed the patient. It has exploited the very openness that made the patient willing to disclose in the first place.
Clinical AI — including consumer health AI — must be evaluated on whether it tells patients what they need to hear, not just what they want to hear. That is the standard that makes a health tool trustworthy. Everything else is entertainment.What physicians can do now
Ask about health apps directly. "Do you use any health apps or AI assistants for health questions?" is now a legitimate intake question. Many patients will say yes. Some will volunteer what they have shared. Others will need to be told that it is clinically relevant.
Create lower-stakes disclosure environments in the clinical encounter. One reason patients disclose to AI instead of their physician is that clinical encounters feel high-stakes. Direct questions — "Is there anything health-related you've noticed in the last few months that you haven't mentioned?" — create an opening that many patients will take if given it.
Recognize the shadow history problem in your differential. When a presentation does not fit, when a patient seems to be downplaying a symptom, when the history feels thin for the clinical picture — consider that the relevant history may exist in a conversation you were never part of.
Advocate for AI tools that route, not reassure. In procurement conversations for consumer-facing health AI tools, ask how the tool handles high-risk symptom disclosures. Ask what the decision logic is for escalating a disclosure to clinical care rather than closing the loop with reassurance. The answer to that question tells you whether the tool was built to help patients or to retain them.
Frequently Asked Questions
Q: Is it a privacy violation for patients to share health information with commercial AI apps?
A: Not typically — patients voluntarily share the information, and most consumer health AI terms of service address data use. The clinical concern is different from the legal one. The problem is not that the patient's privacy was violated. The problem is that the clinical information exists outside the care relationship, with no mechanism to connect it to the physician who needs it.
Q: Should physicians ask patients to share their AI health conversations as part of the medical record?
A: This is an emerging and unresolved question. Some health systems are beginning to explore whether AI-disclosed health information can be incorporated into intake workflows. For now, the practical step is to ask patients directly about health concerns they may have researched or discussed privately — framing it as a clinical history question rather than a technology audit.
Q: What makes a consumer health AI trustworthy versus one that creates clinical risk?
A: Three criteria matter most. First, does it recognize high-acuity symptom patterns and respond with appropriate urgency rather than generic reassurance? Second, does it route concerning disclosures toward clinical care rather than closing the loop itself? Third, does it explain its reasoning in a way that helps the patient understand why action is warranted — not just tell them what to do? A tool that optimizes for user comfort over clinical accuracy is not a health tool. It is a liability.
Q: Does the AI disclosure effect apply equally across age groups and demographics?
A: The research suggests disclosure rates to AI are generally higher across most demographics, but the specific patterns vary. Younger patients tend to use health AI more frequently and may normalize AI-first health disclosure earlier. Older patients — the population at highest cardiovascular risk — may be less likely to use health AI, but when they do, they may be more likely to disclose serious symptoms they have withheld from family and physicians due to social role pressures. The 54-year-old shoveling scenario is not an outlier. It is a demographic archetype.
Q: If an AI gives a patient dangerously inadequate guidance and the patient is harmed, who is liable?
A: This is active legal territory. Most consumer health AI terms of service disclaim medical advice liability explicitly. Whether those disclaimers hold when a tool accepts what is effectively a clinical disclosure and responds with guidance the patient acts on — or fails to act on — has not been tested broadly in courts. The liability question is evolving, but it should not be the reason AI companies build safety into their products. Clinical safety should be the reason.
Dr. Adarsh K. Gupta, DO, MS is a clinical AI strategist and the author of The Science of Habits, where the Habit Cycle (TCAR) framework was first developed. He is a Cochrane Associate Editor with 25+ years of clinical experience. Follow him at adarshgupta.com and subscribe to the Clinical AI Brief for biweekly analysis of clinical AI tools, safety, and adoption.